What the Anion Gap Measures in Critical Care
The anion gap is a fast, hands-on way to measure acid-base balance using routine electrolytes from the serum chemistry panel. In intensive care, it helps recognize an underlying metabolic acidosis and aids early cause identification when a patient is unstable, ventilated, septic, or otherwise physiologically stressed.
An anion gap calculator is useful because it translates a standard lab pattern into bedside action. Rather than looking at sodium, chloride, and bicarbonate as isolated values, the clinician can assess them together as a marker of an acidotic state, anion deficit, or broader metabolic derangement. That makes the result important for diagnostic support and risk stratification.
Physiologically, the anion gap reflects the difference between measured cations and measured anions in the bloodstream. Unmeasured anions such as lactate, ketones, and certain toxins can accumulate, shifting acid-base balance. In contrast, changes in chloride can hide a problem and produce a normal anion gap even when acidosis is present. Because of that, clinical interpretation must always include the full laboratory result and the bedside context.
For critical care, the anion gap is not a stand-alone diagnosis. It is a screening clue that often points toward lactic acidosis, ketoacidosis, renal failure, or toxic ingestion. It can also help differentiate a primary acid-base disorder from a compensatory response. Used well, it becomes part of a systematic approach to acid-base disorder recognition.
How to Use an Anion Gap Calculator
An anion gap calculator uses a basic anion gap formula based on routinely ordered serum values. The usual calculation is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some laboratories or clinicians may use different versions that include potassium, but the sodium-based version is the standard for bedside assessment. The key is to use the same method consistently and interpret the laboratory result in the context of the reference interval used by that lab.
Because the calculation is built from sodium, chloride, and bicarbonate, it is often available whenever an electrolyte panel is ordered. This creates an efficient tool for rapid clinical interpretation in critical care, especially when a patient is deteriorating and immediate trend monitoring matters.
Step-by-Step Calculation Inputs
To use the calculator correctly, enter the following values from the patient’s serum chemistry:
- Serum sodium: the recorded sodium concentration Serum chloride: the measured chloride concentration Serum bicarbonate: the bicarbonate level or total CO2, depending on the laboratory
Once these are entered, the calculator determines the anion gap automatically. In use, this is a quick bedside workflow: review the electrolyte panel, confirm units, and calculate the gap before moving to broader diagnostic support. If the patient has severe illness, the number should be interpreted alongside other signs of perfusion, ventilation, and organ function.
An important point is that serum bicarbonate may be altered by respiratory compensation or prior treatment. Therefore, the number should not be interpreted in isolation. It reflects the current serum chemistry pattern, but the broader acid-base disorder https://anion-gap-estimator327.wpsuo.com/what-is-the-way-kidney-disease-affects-the-anion-gap may be more complex.
Reading the Result at the Bedside
Interpreting the result begins with the normal range used by the laboratory. Although the exact reference interval can vary, a typical range is often around 8 to 12 mEq/L without potassium or slightly higher with different methods. Because laboratory variation exists, the clinician should always rely on the local reference interval rather than a memorized value alone.
A high anion gap points to accumulation of unmeasured anions and backs up the diagnosis of acidic metabolic disturbance. This matters particularly in intensive care, where high lactate, ketones, renal dysfunction, or toxic ingestion may call for immediate intervention.
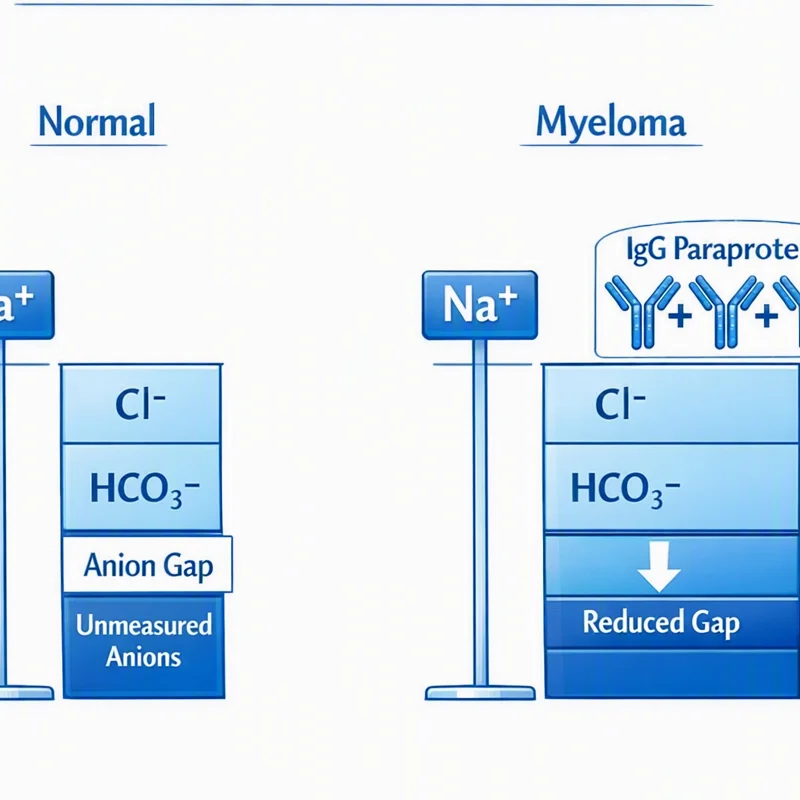
A low anion gap is less common, but it can still be important. It may suggest hypoalbuminemia, laboratory variation, paraproteinemia, or uncommon measurement issues. In some cases, a low value is a clue that the apparent acid-base balance is being distorted by changes in albumin or other serum proteins.
Bedside interpretation should answer three questions: Does the gap fall outside normal limits? Is metabolic acidosis present? And does the pattern suggest a single process or a mixed acid-base disorder? That framework makes a number into useful clinical interpretation.
Adjusting the Anion Gap for Albumin
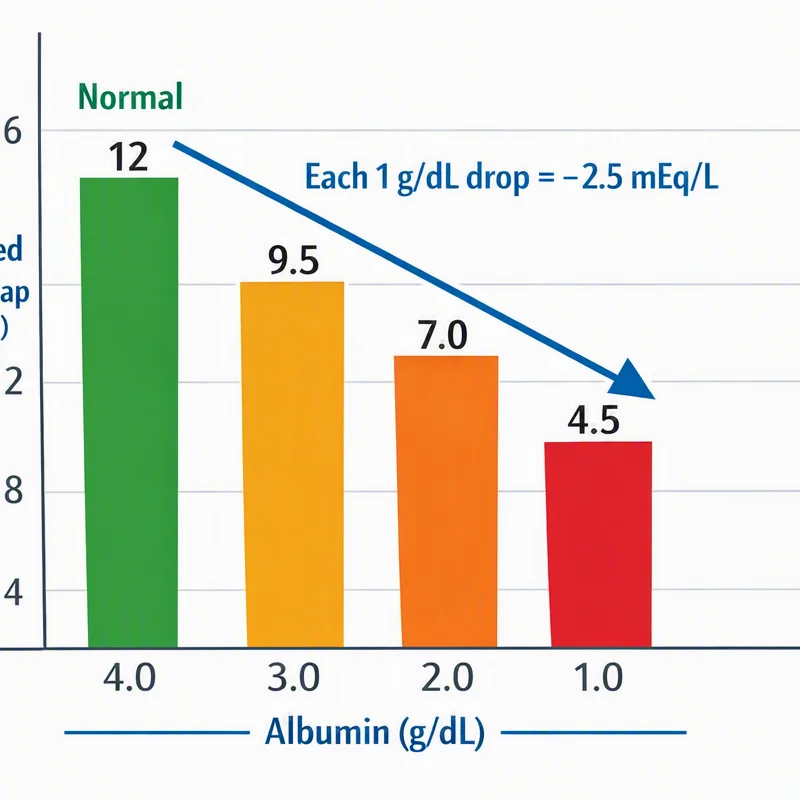
Because albumin is a key unmeasured anion, low albumin can cause the anion gap appear artificially normal or just elevated. For this reason albumin correction is essential in critical care, where hypoalbuminemia is common due to inflammation, fluid shifts, dilution, and illness severity.
The corrected anion gap takes into account hypoalbuminemia and helps identify hidden acidosis. When the patient’s albumin is low, the measured gap may underestimate the true burden of unmeasured anions. That means, a “normal” number can conceal a clinically important acidotic state.
Different institutions may use different correction factors, but the core idea is the same: lower albumin lowers the expected anion gap. When albumin is reduced, adding a correction term can refine risk stratification and sharpen cause identification. This is especially useful when evaluating sepsis, shock, malnutrition, cirrhosis, or prolonged critical illness.
When applying albumin correction, always interpret the result with the overall clinical picture. A corrected anion gap can reclassify a patient from normal anion gap to high anion gap metabolic acidosis, which may change the workup and urgency of care. This is why albumin should be checked whenever the numbers and the bedside picture do not match.
High Anion Gap Metabolic Acidosis: Key Causes
A high anion gap points to excess unmeasured acids in the blood and is a common sign of metabolic acidosis. In acute care, the leading causes often show up early during bedside assessment because they are tied to shock, impaired perfusion, or acute metabolic stress.
Lactic acidosis is one of the most important causes. It may occur with sepsis, hypoperfusion, hypoxemia, seizures, or medication-related metabolic derangement. An elevated lactate should prompt urgent assessment of circulation, oxygen delivery, and source control when appropriate.
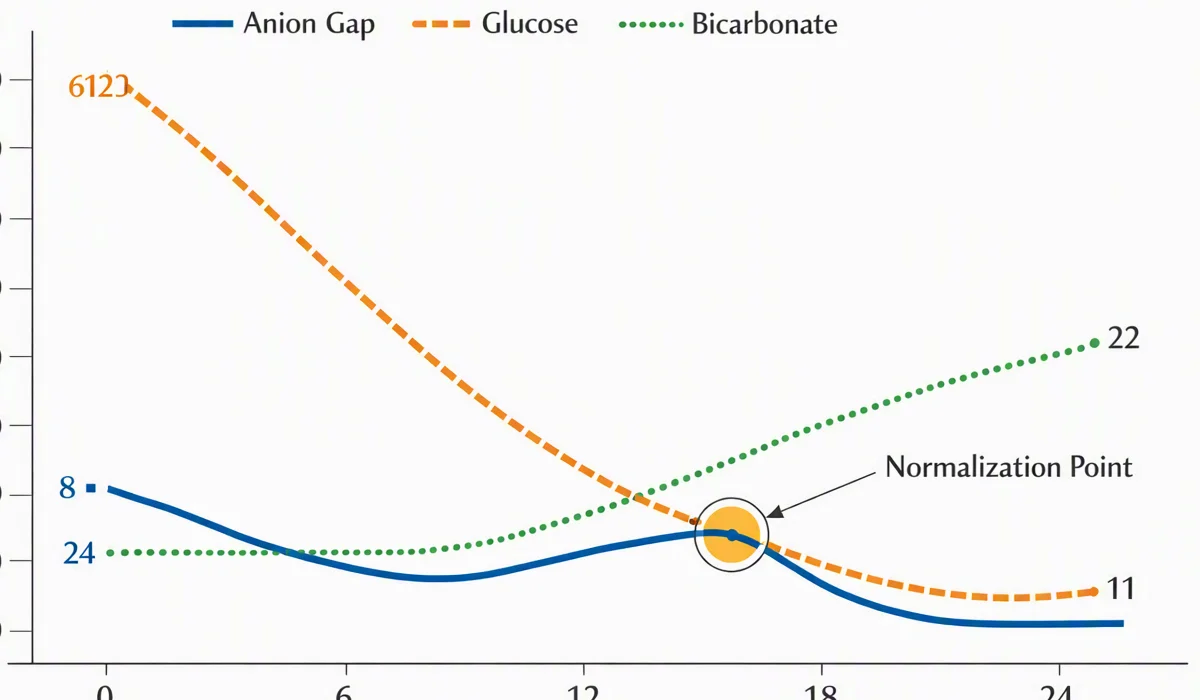
Ketoacidosis is another major cause, including diabetic ketoacidosis, starvation ketosis, and alcoholic ketoacidosis. These states create a high anion gap through accumulation of organic acids. In the ICU, the history, glucose pattern, and ketone measurements help define the diagnosis.
Renal failure can produce high anion gap acidosis by limiting acid excretion and allowing unmeasured acids to accumulate. This can develop acutely or worsen on top of chronic kidney disease. Worsening creatinine, oliguria, and electrolyte shifts often support the diagnosis.
Toxins must also be considered, especially in unexplained or severe cases. Toxic ingestion may involve salicylates, toxic alcohols, or other agents that create a marked metabolic acidosis. When the history is unclear, the gap can provide an early clue that life-threatening exposure is present.
In practice, a high gap should prompt rapid review of perfusion, oxygenation, renal function, glucose, ketones, and exposure history. The value itself is not the endpoint; it is a signal to identify the underlying process and respond quickly.
Normal Anion Gap Metabolic Acidosis and Diagnostic Considerations
A normal anion gap does not exclude acidosis. Rather, it often points toward hyperchloremic acid-base disturbance, where bicarbonate is lost or substituted by chloride, leaving the gap within the reference interval. This finding is common in critical care and can be just as important as a high gap disorder.
Loose stools is a classic cause because gastrointestinal bicarbonate loss drives a non-gap acidosis. Large-volume stool losses can swiftly alter acid-base balance, especially when compounded by poor intake, shock, or kidney injury.
RTA is another key diagnosis. It reflects impaired acid handling in the kidneys and may appear with a normal anion gap despite ongoing metabolic acidosis. The clinical context, urine studies, and serum chemistry trends help separate renal tubular causes from gastrointestinal bicarbonate loss.
The differential diagnosis for normal gap acidosis also includes iatrogenic chloride load, such as large-volume saline resuscitation, and early renal dysfunction. In critical care, these patterns are often mixed, so the clinician should avoid assuming that a normal anion gap means the problem is minor or resolved.
At the bedside, the main question is whether bicarbonate has fallen because it was lost or because another ion shifted in to keep electroneutrality. That framework helps separate hyperchloremic metabolic acidosis from high gap disorders and supports next steps in treatment.
Pitfalls, Drawbacks, and Clinical Setting
Despite that a properly computed anion gap can mislead if the patient context is overlooked. A key concern is lab variation. Different analyzers and methods may produce slightly different reference interval boundaries, so the same patient can appear normal in one system and abnormal in another.
Another major limitation is the complex acid-base disturbance. A patient may have both an increased anion gap metabolic acidosis and metabolic alkalosis, or a high gap process plus respiratory compensation that changes the serum bicarbonate. In these cases, the anion gap alone may fail to capture the complexity of the acid-base imbalance.
The delta-delta is valuable when a high anion gap is present and you want to know whether another process is also occurring. By assessing the rise in anion gap to the fall in bicarbonate, the delta gap can uncover hidden metabolic alkalosis or additional non-gap acidosis. This is especially useful in critical care, where multiple processes often interact.
Albumin remains one of the most common confounders. Low albumin can disguise a major anion deficit, while hemoconcentration can move the result in the opposite direction. Clinical interpretation should therefore pair the electrolyte panel with albumin, renal data, perfusion markers, and bedside examination.
Finally, the anion gap is a metric for diagnostic support, not a standalone answer. It should inform cause identification, prompt serial monitoring, and improve prioritization, but it cannot take the place of a full acid-base assessment.
When to Retest Labs and Advance Care
Monitoring changes is important when the anion gap is outside normal limits or the patient’s condition is changing. A single laboratory result provides a brief picture, but serial monitoring shows whether the metabolic derangement is improving, declining, or responding to therapy.
Recheck labs promptly when the patient has shock, severe infection, worsening renal function, altered mental status, persistent tachypnea, or suspected toxic ingestion. In critical care, these are signs that the acid-base balance may shift rapidly and that the original laboratory result may be insufficient.
An arterial blood gas is commonly indicated when the serum chemistry and the bedside picture do not align. It helps assess pH, respiratory compensation, oxygenation, and the broader acid-base disorder. Together with the electrolyte panel, it provides a better-rounded view of the patient’s physiology.
Increase the level of care when the gap is rising, lactate remains elevated, bicarbonate continues to fall, or the clinical status deteriorates despite treatment. A worsening gap in critical illness can indicate ongoing hypoperfusion, inadequate source control, progression of renal failure, or unresolved toxic ingestion. Early reassessment supports timely intervention and safer decision-making.
Frequently Asked Questions Concerning Anion Gap Calculation
Why use an anion gap calculator used for?
An anion gap calculator is meant to quickly calculate the anion gap from serum sodium, serum chloride, and serum bicarbonate. In critical care, it helps identify metabolic acidosis, point to possible causes such as lactic acidosis or ketoacidosis, and support bedside assessment when rapid clinical interpretation is needed.
What is the normal anion gap range?
The normal anion gap range varies by the laboratory reference interval, but many labs report a typical range around 8 to 12 mEq/L when potassium is excluded. Because laboratory variation exists, the most accurate approach is to use the reference range provided with the patient’s result.
How do you correct anion gap for albumin?
To correct the anion gap for albumin, you apply an albumin correction formula that accounts for hypoalbuminemia. Since albumin is an unmeasured anion, low albumin can make the measured gap look lower than it really is. The corrected anion gap gives a better estimate of the true acid-base burden.
Why is there a high anion gap in critical care patients?
Common causes of a high anion gap in critical care include lactic acidosis, ketoacidosis, renal failure, and toxins. These conditions increase unmeasured acids in the blood and often require urgent evaluation. The anion gap should be interpreted alongside the clinical picture, lactate, ketones, kidney function, and any concern for toxic ingestion.
Can a normal anion gap still indicate metabolic acidosis?
Yes. A normal anion gap can still indicate metabolic acidosis, especially hyperchloremic metabolic acidosis. This pattern may occur with diarrhea, renal tubular acidosis, or chloride-rich fluid administration. A normal gap does not rule out acid-base disorder; it only suggests that the type of acidosis may be different.