What the Anion Gap Measures
The anion gap is a lab-derived metric used to support the assessment of acid-base balance by comparing the major electrolytes in a blood sample. It is typically derived from a serum chemistry panel, which includes key values such as sodium, chloride, and bicarbonate. Because these values reflect the body’s charged particles, the result can offer helpful diagnostic support when clinicians are trying to understand a metabolic disturbance.
More specifically, the anion gap estimates the difference between measured positively charged ions and measured negatively charged ions in the blood. That difference reflects the presence of unmeasured anions, which can rise in certain conditions such as metabolic acidosis. This makes the anion gap a practical tool for checking acid-base homeostasis and identifying patterns that may suggest electrolyte imbalance or other systemic issues.
An anion gap calculator makes this process faster by turning a few lab values into a calculated value that can be reviewed in context. While the calculator does not diagnose disease on its own, it helps organize the information needed for clinical interpretation. In kidney-related evaluation, that can be particularly important because the kidneys play a central role in maintaining the body’s buffer system and controlling acid excretion.
Using an Anion Gap Calculator
Using an anion gap calculator is straightforward. You enter the lab values for sodium, chloride, and bicarbonate, and in some cases albumin if the tool includes an adjustment. The calculator then applies the formula and gives the result, which can be compared with the expected reference interval or lab results from a specific laboratory.
The basic inputs are commonly taken from a standard blood chemistry report. Sodium is usually the largest measured cation, chloride is a major measured anion, and bicarbonate reflects the blood’s buffering capacity. Albumin is important because it is a major negatively charged protein in the blood and can alter the calculated result when it is low.
To use the calculator properly, review the exact values from the report rather than estimating them. Small differences in the numbers can affect the final result, particularly when the value is near the cutoff between a normal gap and an increased gap. If the calculator offers an albumin-adjusted result, enter albumin as well to get a more complete picture.
A simple way to view the process is:
- Enter sodium from the serum chemistry panel. Enter chloride from the same panel. Provide bicarbonate from the same panel. Include albumin if the calculator supports albumin-adjusted output. Assess the result alongside the rest of the labs and symptoms.
This structured approach supports kidney disease evaluation by helping identify whether the lab pattern fits an acid-base disorder that needs more attention.
Anion Gap Calculation and Reference Range
The standard anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
Some laboratories use variations of this equation, and some calculators incorporate potassium or albumin correction. This means, the exact number may differ slightly depending on the method used. The final result is usually reported in mEq/L, a unit that describes concentration in a way that helps compare ions in the blood.
The normal range for anion gap can vary based on the laboratory’s lab reference range. Because methods and measurement platforms differ, one lab may define a normal result differently from another. This is why the result should always be interpreted against the specific reference interval listed with the test report.
In general, a higher-than-expected value may suggest an accumulation of unmeasured acids, while a reduced value may point to issues such as low albumin or certain measurement differences. The calculator offers a helpful starting point, but the number alone does not tell the full story.
When reviewing results, it is useful to remember that the anion gap is not a stand-alone diagnosis. It is a calculated value that helps narrow the possibilities and guide more focused medical evaluation. In that sense, it is best viewed as a preliminary and assessment tool rather than a final answer.
The reason the Anion Gap Is Important in Kidney Function
The connection between kidney function and the anion gap is medically important because the kidneys control acid removal and bicarbonate balance. When kidney performance declines, acids may build up in the body, heightening the risk of metabolic acidosis. This is a key reason the anion gap is often included in kidney disease evaluation and broader metabolic workups.
In chronic kidney disease, the kidneys may struggle to excrete acid effectively or restore enough bicarbonate. As a result, the blood can become acidic over time. In more advanced renal failure, the buildup of retained acids may produce a higher anion gap and strengthen the suspicion of uremia, a condition associated with the accumulation of waste products in the blood.
The anion gap can also help separate the type of acid-base problem present. Some kidney-related disorders lead to a high gap, while others cause a normal gap acidosis. That distinction counts because it can point toward different mechanisms, such as acid retention, bicarbonate loss, or impaired tubular handling of electrolytes.
For people with known kidney disease, the calculator can be a useful way to review whether the chemistry panel suggests worsening renal impairment or a new metabolic disturbance. Still, it should always be reviewed with the rest of the clinical picture, including hydration status, medications, and the trend in prior blood tests.
Frequent Causes of a High Anion Gap
A high anion gap typically indicates there are more acids in the blood outside what is normally assessed. This creates an increased gap and may point to a serious metabolic problem. Several frequent causes are highly relevant when evaluating acid-base balance and kidney function.
Lactic acid accumulation is a major cause. It occurs when lactate builds up, often due to inadequate oxygen supply, shock, infection, or other systemic stress. Because lactate is an unmeasured anion, it can push the gap higher significantly.
Acid buildup from ketones is another important cause. It can occur when the body produces excess ketones, often in uncontrolled diabetes, starvation states, or alcohol-related metabolic changes. These ketones contribute to systemic acidosis and push the anion gap upward.
Uremia from advanced kidney dysfunction can also increase the gap. As the kidneys lose the ability to clear metabolic acids, unmeasured anions collect. This is a key reason the anion gap is useful in severe kidney dysfunction and chronic kidney disease.
Toxic alcohols are another serious consideration in a high-gap pattern. Ingestion of substances such as methanol or ethylene glycol can cause dangerous acid buildup and requires urgent medical attention. In these cases, the calculator may help identify an abnormal pattern, but it cannot determine the exact toxin.
Overall, a high result may point toward one of several metabolic problems:
- lactic acidosis ketoacidosis renal toxin buildup alcohol toxins
The value should be treated as a sign that guides additional testing and clinical interpretation.
Frequent Causes of a Normal Anion Gap
A regular anion gap does not always mean all is well. It can still be seen in serious acid-base conditions, especially when bicarbonate is lost and chloride increases to compensate. This is often called hyperchloremic acidosis, a pattern in which the anion gap stays normal even though acid-base balance is disturbed.
Diarrhea is a frequent cause because the body can lose bicarbonate through the gastrointestinal tract. That bicarbonate loss lowers buffering capacity and may cause acidosis without creating extra unmeasured anions. In this setting, chloride often goes up to keep electrical balance.
Renal tubular acidosis is another major cause. This kidney-related disorder happens when the renal tubules do not handle acid and bicarbonate properly. Even though kidney function may not be globally failing, the tubular defect leads to a normal gap acidosis pattern that can be detected through careful lab review.
These conditions show why the anion gap should be considered alongside other electrolytes and symptoms. A normal value does not rule out disease. It merely suggests that the cause of acidosis may be different from the one seen in high-gap states.
Serum albumin Adjustment and Why It Matters
Albumin has a major effect on the anion gap because it is a negatively charged protein that contributes to the body’s general charge balance. When albumin is low, the measured anion gap may appear artificially low than it truly is. This is why hypoalbuminemia can mask an serious acid-base disorder.
To adjust for that effect, clinicians may use a corrected anion gap. This albumin correction adjusts the calculated value so that low albumin does not conceal an underlying increase in unmeasured anions. The result is often more useful when evaluating patients with chronic illness, inflammation, malnutrition, or kidney disease.
An albumin-adjusted result can be highly valuable because low albumin is common in people with reduced kidney function or systemic illness. If the uncorrected number looks normal but the albumin is low, the corrected value may uncover a clinically important increase in the gap. That difference can change the interpretation of the lab-derived metric entirely.
In practical terms, albumin correction improves the accuracy of the calculator and supports better medical interpretation. It helps distinguish a truly normal result from one that only appears normal because the protein level is reduced.
How to Read Results in Situation
An anion gap result should never be read in separation. The number becomes useful when combined with lab tests, the clinical picture, and the person’s current signs. This is especially true when evaluating possible acid-base disorder or kidney-related metabolic disturbance.
For instance, if a person has nausea, rapid breathing, confusion, or weakness, an abnormal gap may point to a more urgent concern. If the same result appears in someone with stable health and no symptoms, the interpretation may be less concerning. The calculator provides a derived value, but the clinician determines what that value means within the overall picture.
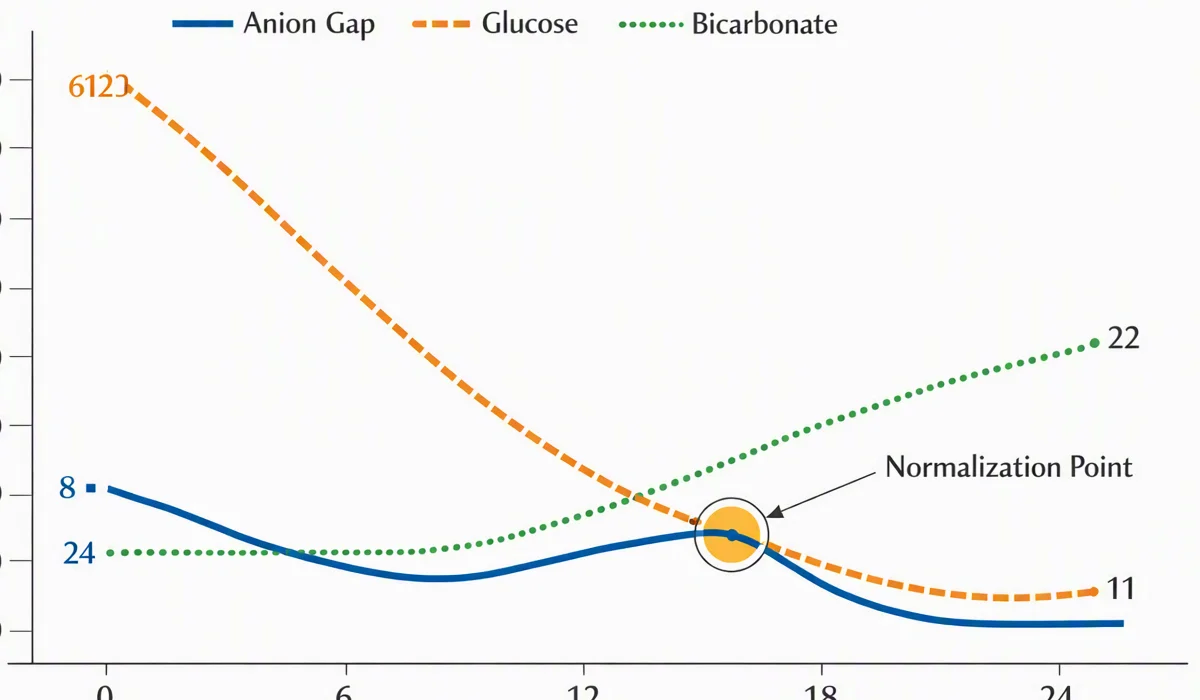
It also helps to review related findings such as creatinine, blood urea nitrogen, glucose, lactate, ketones, and chloride trends. Those values can clarify whether the abnormality reflects renal function decline, a systemic acid load, or a separate metabolic issue. This broader review is a core part of effective medical interpretation.
In many cases, the anion gap is just one piece of a larger diagnostic puzzle. It can point toward the presence of systemic acidosis, but additional testing is often needed to identify the underlying cause and determine the appropriate next steps.
Drawbacks of an Anion Gap Calculator
Even a good anion gap calculator has constraints. The result is only as accurate as the numbers entered, and input error can affect the output. Small differences in sodium, chloride, or bicarbonate may change the calculated result enough to alter interpretation, especially when values are near the cutoff.
Lab variability is another concern. Different laboratories may use different analyzers, reporting methods, and calculation approaches. That means one lab’s reference intervals may not match another’s. A result that seems abnormal in one setting may fall within the expected range in another.
For this reason, the calculator should be used for support, not as the single foundation for decision-making. The number is a derived result, not a literal measurement. It can suggest patterns, but it cannot determine the cause of a disorder by itself.
There are instances where the gap may be misleading. Decreased albumin, unusual proteins, or technical lab issues can obscure the true picture. That is why careful clinical interpretation remains essential, especially when symptoms or kidney function tests do not match the calculator result.
When to Seek Medical Evaluation
It is important to seek medical evaluation if https://privatebin.net/?6a5c1f33485a37a0#26aHQCBVP2MJNU6vPmifWD3qBiDEjLuP6kv6QwkcUF9M an abnormal anion gap appears along with serious symptoms or signs of illness that could reflect a serious acid-base problem. These may include fast breathing, vomiting, confusion, chest pain, marked weakness, or dehydration. A sudden change in how you feel can matter as much as the number itself.
Individuals with established kidney disease or worsening renal impairment should also review abnormal results with a clinician. A nephrologist may be especially helpful if the abnormality is persistent, unexplained, or tied to chronic kidney disease. Kidney-related acidosis can require targeted treatment and close follow-up.
If the result is significantly abnormal and symptoms are progressing, urgent care or emergency evaluation may be appropriate. This is particularly important when the pattern suggests lactic acidosis, ketoacidosis, toxic alcohol exposure, or advanced uremia. A calculator can highlight risk, but it cannot replace direct care when symptoms are concerning.
In short, the anion gap is a valuable support tool for kidney function assessment, but it works best as part of a broader medical review. Persistent abnormalities deserve professional attention.
FAQs About Anion Gap and Kidney Assessment
What is an anion gap calculator used for?
An anion gap calculator is used to calculate the anion gap from lab values such as sodium, chloride, and bicarbonate. It helps assess electrolytes, support kidney function review, and identify possible metabolic acidosis or other acid-base problems. It is a helpful tool for organizing lab results, but it does not replace medical evaluation.
How does anion gap relate to kidney function?
The anion gap connects with kidney function because the kidneys support the regulation of acid removal and bicarbonate balance. When kidney function declines, acids can build up and cause metabolic acidosis. This can result in an increased gap, especially in chronic kidney disease, renal failure, or uremia.
What would be a normal anion gap range?
The normal range depends on the laboratory’s lab reference range and the method used. Results are typically reported in mEq/L. Because different labs use different analyzers and reference intervals, you should compare the result with the range printed on the report rather than relying on a single universal cutoff.
Why should albumin be used to correct the anion gap?
Albumin needs to be used in assessment because low levels can lower the measured gap and mask a real abnormality. In hypoalbuminemia, a adjusted anion gap or albumin adjustment gives a better assessment of the real acid-base status. This is especially useful when assessing chronic illness or kidney disease, where albumin may be reduced.
Can a normal anion gap still mean a kidney problem?
Indeed. A standard gap can still occur with kidney-associated issues such as renal tubular acidosis or initial acid base disturbances that do not yet produce a raised gap. It can also show up in hyperchloremic acidosis caused by bicarbonate loss. So a normal result does not rule out renal issues; it just indicates a different pattern that calls for clinical evaluation.