What’s the anion gap?
The anion-gap value is a calculated result used to assist in interpreting electrolyte levels and assess acid-base status. It compares the main measured positively charged ions, especially sodium, with the measured negative ions, mainly Cl and HCO3. This straightforward laboratory calculation can reveal whether there are additional acids or other hidden anions affecting the body’s internal chemistry.
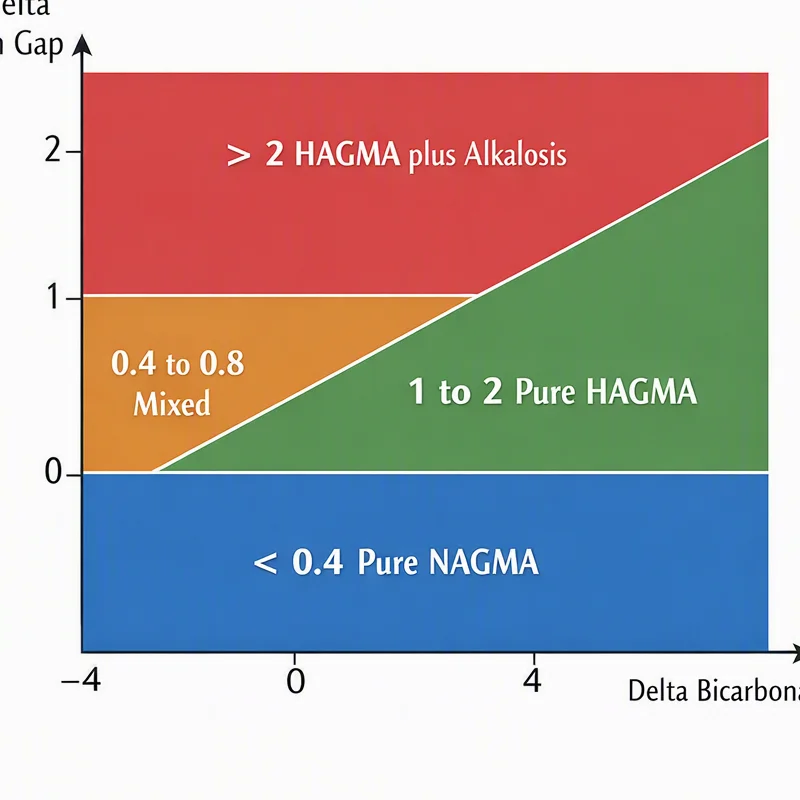
Clinically, the anion gap is a useful diagnostic aid for spotting an underlying metabolic abnormality. It is often reviewed as part of a broader electrolyte panel or blood chemistry assessment. Although the value is not a diagnosis by itself, it can indicate an acid-base disorder that requires further investigation.
The basic idea is straightforward: if the difference between the measured cations and anions is higher than expected, the extra gap often reflects acids that are not directly measured on routine labs. That is why the anion gap plays a key role in anion gap interpretation and in evaluating acidosis.
How Albumin Affects the Anion Gap
Albumin is as one of the most significant unmeasured anions within the blood. Because albumin carries a negative charge, it plays a role significantly to the usual gap seen on chemistry testing. When serum albumin is low, the anion gap may look falsely low even if important acids are present.
Here hypoalbuminemia becomes clinically important. In people with low albumin, the measured anion gap can underestimate the severity of an acid-base problem. A patient may have significant retained acids, but the lab value can look deceptively normal because the negative charge from albumin has been reduced.
This occurs is related to protein charge. Albumin normally helps stabilize the electrical environment in plasma. If albumin drops, the body compensates in ways that can shift chloride and other ions, changing the appearance of the gap. For this reason clinicians often use an albumin correction or an albumin-adjusted anion gap to improve diagnostic accuracy.
Using the correction helps with clinical utility because it makes the result more useful when evaluating a possible electrolyte imbalance or compensated acidosis. Overall, low albumin can hide the true acid burden, and correcting for it gives a clearer picture of the patient’s acid-base disorder.
Anion Gap Formula and Albumin Correction
The usual anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Some clinical laboratories may use slight variations, but this is the standard structure for a routine lab calculation. The result is then measured against a lab’s reference range to determine whether it is decreased, normal, or elevated.
To account for low albumin, clinicians use an albumin correction formula. A commonly used approach is to add about 2.5 mEq/L to the calculated gap for every 1 g/dL decrease in albumin below 4.0 g/dL. This creates a corrected anion gap that more accurately reflects the patient’s real acid burden.
Corrected anion gap = Measured anion gap + 2.5 × (4.0 - serum albumin in g/dL)
This correction factor is especially helpful in patients with low albumin, because the uncorrected value may look closer to a normal anion gap even when extra acids are present. The goal is not to replace clinical judgment, but to enhance interpretation.
With this adjustment, a hidden high anion gap metabolic acidosis may become easier to recognize. The corrected value can also help distinguish true abnormal acid accumulation from a value that only appears normal because albumin is reduced.
How to Use Anion Gap Calculator
An anion gap calculator makes easier the procedure by combining the key lab values into one result. To operate it, enter the relevant values from the electrolyte panel:
- Sodium level Chloride level Bicarbonate level Serum albumin
The calculator first performs the standard lab calculation for the anion gap. Then it uses albumin correction to produce the corrected anion gap. This helps to calculate anion gap values quickly while also factoring in serum albumin abnormalities.
In practical use, the calculator supports quicker interpretation of serum electrolytes and helps clinicians decide whether the pattern suggests a metabolic acidosis. It is especially useful in cases where the acid-base picture is complex, the patient has significant illness, or the laboratory data point to mixed disorders.
For example, a patient with low bicarbonate and low albumin may still have a more significant acid burden than the raw anion gap suggests. By using the calculator, the clinician can better assess acid-base status and determine whether the problem is more consistent with elevated unmeasured acids.
Understanding High versus Normal Anion Gap Results
A increased anion gap metabolic acidosis usually means that extra acids are present in the bloodstream. These acids raise the gap because they are not directly measured on routine chemistry testing. Frequent causes include elevated lactate, ketone body accumulation, renal impairment, and toxic ingestions.
In contrast, a non-anion gap metabolic acidosis is typically associated with loss of bicarbonate or failure to excrete acid without a marked rise in unmeasured acids. Because the uncorrected value may seem normal in the setting of reduced albumin, albumin adjustment is important before concluding that the acid-base picture is truly normal.
Lactic acid accumulation occurs when lactate rises, often due to tissue hypoperfusion, severe illness, or impaired metabolism. Ketone body buildup occurs when ketone bodies build up, such as in diabetes, starvation, or alcohol-related states. Both cause a true elevation in the gap and require prompt evaluation.
The result must be interpreted in context. A corrected value that changes from normal to elevated may revise the entire diagnostic approach. That is the value of anion gap interpretation: it helps clinicians identify whether the acid-base pattern is likely due to excess acids, bicarbonate loss, or a mixed disorder.
Common Causes of Raised Anion Gap
A number of conditions can elevate the anion gap. A primary reason is renal failure, which impairs the body’s ability to remove acid. As kidney function worsens, acids build up and the gap may widen. Related to this is uremia, where retained waste products and acid retention contribute to the abnormal value.
Another key group is toxic alcohols, including substances that produce acid metabolites after ingestion. These can trigger dangerous high-gap acidosis and require immediate recognition. The presence of a high gap in the right clinical setting may help refine the differential diagnosis rapidly.
Lactate is also a major contributor. Elevated lactate may result from shock, infection, https://anion-gap-test918.evergrovio.com/posts/anion-gap-calculation-when-bicarbonate-is-normal hypoxia, seizures, or other conditions that drive anaerobic metabolism. Since lactate is an unmeasured anion on standard panels, it can increase the measured gap significantly.
Further causes of abnormal values include ketone accumulation, medication effects, and other forms of retained acids. The final interpretation should always link the lab pattern to the clinical presentation. In other words, the anion gap is a tool for reasoning through the source of the metabolic acidosis, not a stand-alone answer.
Limitations and Clinical Considerations
Even though the anion gap is useful, it has significant limitations. A result can be altered by measurement error in the underlying electrolyte panel, especially if sodium, chloride, or bicarbonate values are off. Minor lab differences can shift the resulting calculation more than clinicians realize.
Assessing the result also relies on the lab’s reference range. Individual laboratories use different methods and calibration standards, so the “normal” value may differ. A result that looks abnormal in one setting may fall within the expected range in another.
The anion gap should also be interpreted alongside supporting data, including the arterial blood gas when available. The blood gas helps define pH, respiratory compensation, and whether the patient has a mixed acid-base picture. In combination with the chemistry panel, it gives a clearer view of the patient’s acid-base status.
In the end, a corrected value enhances interpretation but does not replace bedside assessment. Clinical context, medications, kidney function, perfusion, and symptoms all matter. The best use of the calculator is as a diagnostic aid that assists, rather than takes the place of, medical reasoning.
Frequently Asked Questions
What is an anion gap calculator with albumin correction?
An anion gap calculator with albumin correction is a utility that calculates the standard anion gap and then adjusts it for serum albumin measurements. This helps produce a more accurate corrected anion gap, especially when albumin is low and the uncorrected value may underestimate the true acid burden. It is commonly used as a diagnostic aid in evaluating metabolic acidosis.
Why do you correct the anion gap for albumin?
You correct the anion gap for albumin because albumin is a major unmeasured anions contributor in blood. In hypoalbuminemia, the raw anion gap can appear lower than expected, which may hide a significant acid-base problem. Albumin correction improves clinical interpretation and helps reveal true anion gap interpretation more accurately.
How do you calculate the corrected anion gap?
First, use the anion gap formula: sodium minus the sum of chloride and bicarbonate. Then apply the albumin correction formula by adding about 2.5 mEq/L for each 1 g/dL that serum albumin is below 4.0 g/dL. This gives the corrected anion gap and helps account for low albumin when you evaluate the result.
What does a high anion gap mean?
A high anion gap usually indicates high anion gap metabolic acidosis, which means there are extra acids in the blood that are not directly measured on routine labs. Common causes include lactic acidosis, ketoacidosis, renal failure, uremia, and toxic alcohols. The result should be interpreted with the electrolyte panel, symptoms, and other clinical data.
Can a standard anion gap even indicate acid-base acidosis?
Absolutely. A normal anion gap metabolic acidosis can also be present, especially if bicarbonate is reduced but the gap remains within the reference range. Moreover, hypoalbuminemia can cause a true high-gap acidosis look normal unless you use corrected albumin value. This is why the corrected value and overall clinical utility of the calculator are so important for accurate acidosis assessment.