What the anion gap measures
The anion gap is a practical way to look at the balance of electrolytes in blood and to assess acid-base balance. It is not a direct test of a single substance. Instead, it is a derived value that reflects the difference between positively charged and negatively charged particles in the bloodstream. Clinicians often use it as a clue when investigating metabolic acidosis and other acid-base disorder patterns.
In clinical terms, the anion gap helps identify whether there may be unmeasured acids or other abnormal substances affecting serum levels. Because it is derived from common lab values, it is a valuable diagnostic tool when reviewing blood test results. The result can point toward an electrolyte imbalance or another metabolic disorder that needs more evaluation.
Although the number itself is simple, its clinical significance depends on the whole picture. A mildly abnormal result may be less concerning than a dramatic change with symptoms. That is why an anion gap should always be considered alongside the patient’s condition, the reference range, and the rest of the chemistry results.
How an anion gap calculator works
An Anion Gap Calculator takes basic lab values to calculate anion gap rapidly and consistently. Typical calculators ask for sodium, chloride, and bicarbonate, which are usually included on a standard chemistry report. By entering those values, the calculator performs the anion gap formula and returns a result that can be checked with the expected reference range.
The reason this is effective is that sodium is the main measured cation, while chloride and bicarbonate make up major measured anions. The difference between them offers a useful estimate of unmeasured ions in the blood. When the gap is widened, clinicians may search for acids that are not directly measured on a routine electrolyte panel.

An Anion Gap Calculator is especially valuable when reviewing complex blood test results or checking whether an abnormal value aligns with the overall pattern. It can support quicker interpretation, but it does not replace clinical judgment. The same number can have another meaning depending on the patient, the lab method, and the other lab values present.
Anion gap formula and calculation examples
The most common anion gap equation is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
The formula relies on serum sodium, serum chloride, and serum bicarbonate from a routine lab result. Some laboratories use a slightly different method, and potassium was included in some older formulas, but the sodium-based version is the version most often used in clinical practice.
Example 1: if the serum sodium is 140, the serum chloride is 102, and the serum bicarbonate is 24, the anion gap is 140 − (102 + 24) = 14. This value may sit inside the normal reference range depending on the method used.
Example 2: if the serum sodium is 138, the serum chloride is 100, and the serum bicarbonate is 12, the anion gap is 138 − (100 + 12) = 26. This higher value raises concern for high anion gap metabolic acidosis and should prompt review of the full clinical picture.
For example 3, if the sodium is normal but bicarbonate is low with a normal gap, this may point toward normal anion gap metabolic acidosis. The calculator helps identify the pattern, but interpretation depends on the cause and associated findings.
Standard anion gap reference range and what changes it
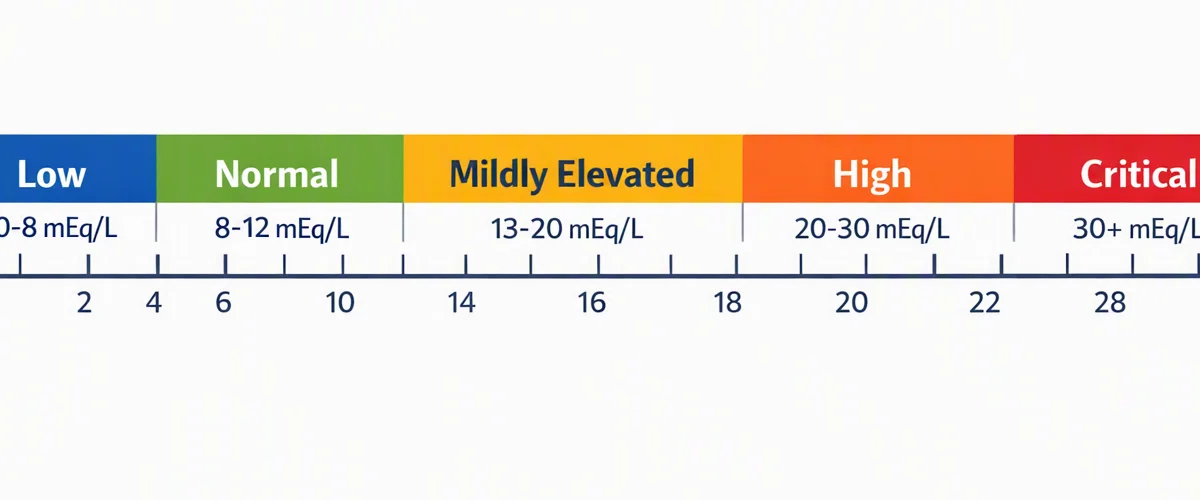
The expected range for anion gap differs by lab because of variations in measurement methods and result standards. For this reason the reference interval listed on the report is more important than a single cutoff. A result that appears high in one lab may be normal in another.
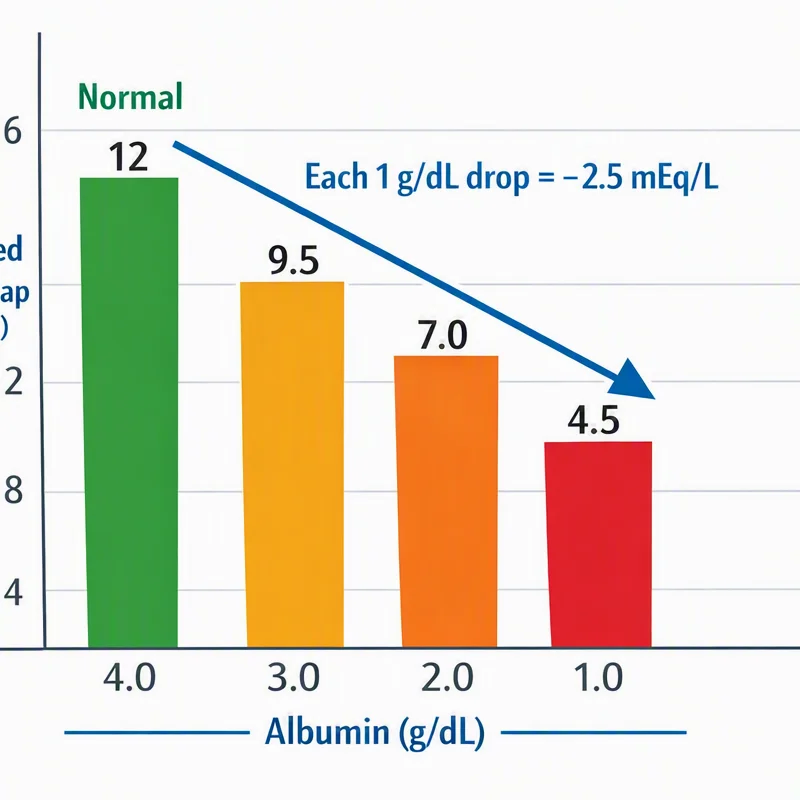
Albumin is one of the most important factors that affects the result. Since albumin is a negatively charged protein, lower albumin levels can make the gap appear smaller than it truly is. In patients with low albumin, albumin correction may be required to better estimate the true gap. One reason a single number should not be interpreted in isolation.
Other influences include alterations in measured cations, shifts in protein levels, and differences in analyzer techniques. Some medications, toxins, and unusual blood proteins can also affect the value. For this reason, interpreting the anion gap is not just a math problem; it is a evaluation of chemistry, context, and pattern analysis.
High anion gap compared with normal anion gap
A raised result often indicates high anion gap metabolic acidosis, which occurs when unmeasured acids build up in the blood. Common causes include lactic acidosis, ketoacidosis, and kidney failure. In these cases, bicarbonate is used up as the body buffers excess acid, and the gap rises because the missing bicarbonate is replaced by unmeasured anions.
Lactic acidosis can occur when tissues do not get enough oxygen, when severe infection is present, or when other systemic stressors drive lactate production. Ketoacidosis is often associated with diabetes, alcohol use, or prolonged fasting. Kidney failure can reduce the body’s ability to clear acids, which also raises the gap.
By contrast, normal anion gap metabolic acidosis usually suggests a loss of bicarbonate rather than buildup of unmeasured acid. Common mechanisms include gastrointestinal bicarbonate loss or renal tubular problems. The gap stays normal because chloride often rises to balance the loss of bicarbonate, even though the patient still has an acid-base problem.
Understanding whether the pattern is high or normal is a major step in the interpretation of the result. Both patterns can signal a serious metabolic disorder, but they point toward different underlying cause pathways and therefore different next steps.
Low anion gap causes along with clinical implications
A decreased anion gap is rarer than a high one, but https://anion-gap-calculation.com/formula/with-potassium.html it can still be medically important. One of the most common causes is hypoalbuminemia, because albumin plays a major role to the unmeasured anions in blood. When albumin is low, the gap may drop even if there is no true acid-base abnormality.
Albumin correction is especially important here. If the albumin is low, a corrected calculation may show that the apparent low gap is mostly accounted for by reduced protein levels rather than a separate disorder. This prevents overcalling an abnormal result and helps identify the real issue.
Other factors include lab artifact, elevated unmeasured positively charged proteins, and certain medications or toxins. Multiple myeloma is a classic clinical association because abnormal immunoglobulins can decrease the gap. Lithium exposure can also reduce the gap because lithium is an unmeasured cation that may change the balance of charged particles.
A low value should not be ignored, but it should also not be read too strongly without the full picture. The result may reflect protein changes, medication effects, or measurement issues rather than a dangerous acid-base problem. That is why review of the full chemistry report and clinical scenario is essential.
How to interpret anion gap in blood test results
Accurate interpretation of blood tests begins with the whole electrolyte panel, not just one number. The anion gap should be viewed together with sodium, chloride, bicarbonate, kidney function, glucose, and other important abnormal results. A single abnormal result may matter less than a consistent pattern across several measurements.
To begin, confirm that the values came from a trusted blood chemistry test and that the reported normal range used by the lab matches the method used by that lab. Next, look at the bicarbonate level. If bicarbonate is low, ask whether the anion gap is high, normal, or low, because that distinction can guide the diagnosis.
Next, consider the clinical context. Symptoms, recent illness, medications, fluid status, kidney function, and nutrition all matter. For example, low albumin from chronic illness can change the interpretation, while signs of infection or poor perfusion may make lactic acidosis more likely. This is where the calculator becomes not merely a mathematical shortcut; it helps with structured clinical reasoning.
It is also important to understand that the anion gap is a screening clue, not a final diagnosis. A result can indicate an acid-base pattern, but it does not by itself identify the exact cause. The right next step may include repeat testing, albumin correction, blood gas analysis, or additional studies based on the scenario.
When to seek medical assessment
Any atypical anion gap should be considered in relation to symptoms and the overall situation. Small shifts without symptoms may simply need monitoring and repeat testing. However, a substantial change from the expected range, especially with low bicarbonate, may indicate severe acidosis that needs urgent attention.
Warning signs including rapid breathing, confusion, severe weakness, vomiting, chest pain, dehydration, or worsening illness can suggest a more concerning problem. In these cases, emergency care may be appropriate, especially if the blood chemistry shows a clear abnormality or the person is visibly unwell.
Physician review is important whenever the result is surprising, persistent, or paired with other concerning findings. This is particularly true if there is known kidney disease, diabetes, toxic exposure, infection, or unexplained changes in mental status. A clinician can relate the lab pattern with symptom assessment and decide whether additional treatment or testing is needed.
FAQ about anion gap blood tests
What is an anion gap calculator used for?
An anion gap calculator is used to rapidly estimate the anion gap from routine blood chemistry values. It helps clinicians and patients understand blood test results, identify possible acid-base disturbances, and decide whether the pattern fits a high, normal, or low gap. It is a practical diagnostic tool, but it works best when paired with the full clinical picture.
How do you calculate anion gap from blood test results?
To calculate anion gap, use the common anion gap formula: serum sodium minus the sum of serum chloride and serum bicarbonate. In other words, serum sodium − ( serum chloride + serum bicarbonate). This can be done manually or with an Anion Gap Calculator using values from a blood chemistry panel.
What does a high anion gap mean?
A elevated result often may indicate high anion gap metabolic acidosis, meaning there may be too much unmeasured acids in the blood. Frequent causes include lactic acidosis, ketoacidosis, and kidney failure. The result should be assessed with other lab values and the patient’s clinical context.
What can cause a low anion gap?
A low anion gap is often associated with hypoalbuminemia, since low albumin reduces the number of unmeasured anions. Other causes include multiple myeloma, lithium exposure, and occasional lab-related issues. If albumin is low, albumin correction may affect the interpretation.
Should albumin be included when interpreting the anion gap?
Yes, albumin should be considered because it significantly affects the result. If albumin is low, the raw number may miss the true gap, which is why albumin correction is often important. Including albumin enhances the accuracy of blood test interpretation and helps minimize missed acid-base abnormalities.