What the Anion Gap Reflects
The anion gap represents a computed value used to help evaluate electrolytes and interpret acid-base balance. It is never a laboratory-measured lab analyte by itself; instead, it is calculated from common values on a serum chemistry panel. Clinicians use it as a diagnostic tool when interpreting lab results for signs of an electrolyte imbalance or an acid-base disorder.
At its foundation, the anion gap shows the connection between major positively charged ions and negatively charged ions in the blood. The usual focus is on serum sodium, serum chloride, and serum bicarbonate, with potassium sometimes added depending on the formula being used. Because many unmeasured ions also add to the total anion concentration, the anion gap offers an interpretive framework for finding hidden causes of metabolic acidosis.
In practical terms, the anion gap helps identify whether acid is accumulating in the body, whether bicarbonate is being lost, or whether another process is affecting the balance of charged particles in the bloodstream. That makes it especially useful in metabolic evaluation and clinical assessment.
Formula for Anion Gap With and Without Potassium
There exist two standard approaches to calculate the anion gap: a traditional formula that leaves out potassium and a potassium-based formula that puts it back. An anion gap calculator may work with either formula, so it is useful to know which one is being applied.
The traditional formula is:
Anion gap result = sodium - (Cl + bicarbonate)
The potassium-inclusive formula is:
Anion gap = Na + potassium - (chloride + HCO3)
This difference may seem slight, but it can change the final value of the anion gap. Since potassium is usually present in a lesser concentration than sodium, the numeric change is limited, yet it can matter when comparing results across different lab systems or when tracking a borderline value.
Some clinicians prefer the version without potassium because it is more often used in modern practice. Others include potassium because it reflects a more complete charge balance and can be helpful in select situations. Either way, the most important step is to know which equation your calculator uses and to read the result accurately.
How to Calculate the Anion Gap Step by Step
To work out the anion gap, use the relevant test results from the blood chemistry panel. You need serum sodium, serum chloride, and serum bicarbonate; potassium is optional depending on the formula. Using the right equation matters because a calculator cannot compensate for mismatched inputs and formula assumptions.
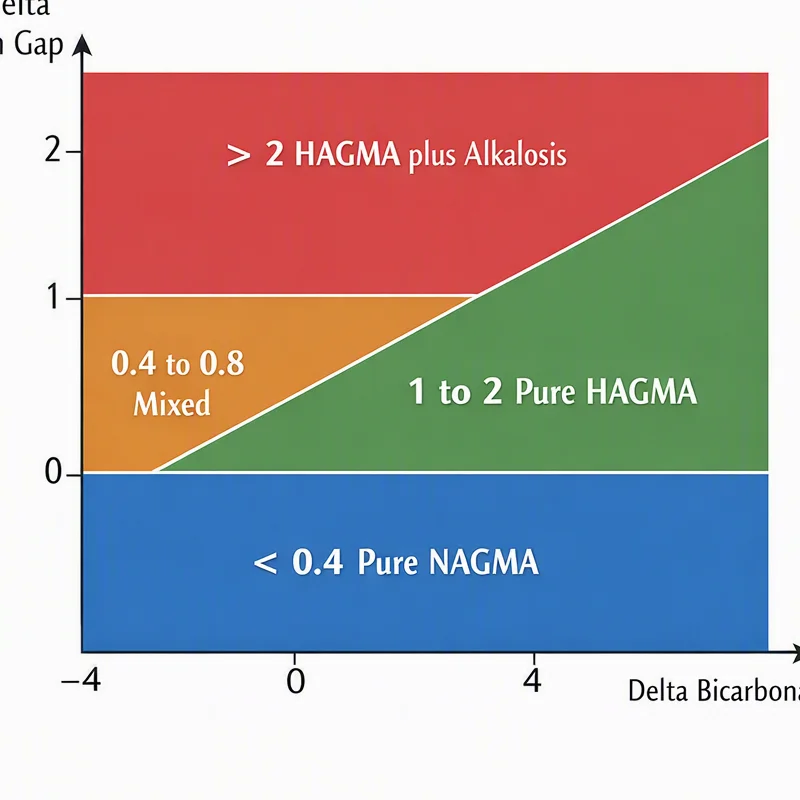
Here is a simple stepwise process:
- Identify the sodium value on the chemistry panel. Find the chloride value. Identify the bicarbonate value, often listed as CO2 or total CO2. Choose between the traditional formula or the potassium-inclusive formula. Type in the numbers into the calculator or calculate manually. Review the result with the lab reference range used by that laboratory.
Here is an example with the traditional formula:
If sodium is 140, chloride is 102, and bicarbonate is 24, then:
140 - (102 + 24) = 14
An example using potassium-inclusive formula:
If sodium is 140, potassium is 4, chloride is 102, and bicarbonate is 24, then:
140 + 4 - (102 + 24) = 18
That difference shows why the calculator should clearly identify whether it is reporting an uncorrected anion gap or a potassium-inclusive result. Either way, the value is only one part of the overall metabolic picture.
Typical Anion Gap Range and What Outside-the-range Results Mean
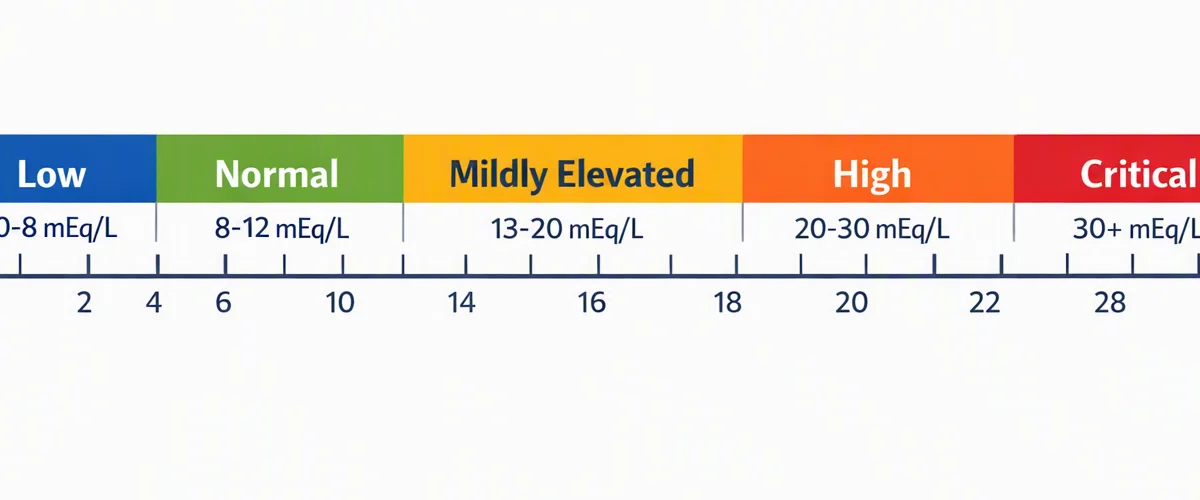
The reference range for the anion gap depends on the local reference range and the specific calculation method. Different laboratories may report different reference interval values because of their testing methods and whether they include potassium.
A high anion gap usually suggests that additional acidic substances are present in excess. This pattern is often seen in metabolic acidosis caused by build-up of acid. A standard anion gap, on the other hand, can still occur in acidosis if bicarbonate loss is matched by chloride gain, producing a different biochemical pattern.
Interpretation should never rely on a single number alone. A mildly elevated value may be insignificant in one context but important in another, especially if the patient https://anion-gap-estimator957.swiftnestly.com/posts/exploring-albumin-corrected-anion-gap has symptoms or other abnormal lab findings. The exact meaning depends on the patient’s clinical interpretation and the surrounding data.
It is also important to compare the calculated result with the local lab reference range rather than a generic number from another source. The same anion gap value may be normal in one system and abnormal in another.
The reason Potassium May Be Included in the Formula
Including potassium in the equation is based on the idea of charge balance. In body fluids, opposing charges must be equal. Because potassium is a measured cation, counting it to the formula gives a more full picture of the major ions contributing to the total charge balance.
From a practical standpoint, potassium inclusion may enhance certain aspects of clinical interpretation, especially when a clinician wants to compare the result with older literature or with settings that still use the potassium-inclusive version. It can also be helpful when reviewing borderline values or when following a patient over time using the same formula.
That said, many modern references support the traditional formula because potassium contributes a smaller amount to the total than sodium and because excluding it makes easier routine use. The best choice depends on the purpose of the calculation, the calculator settings, and the local reporting practice.
When using any anion gap calculator, stability matters more than preference. If you change formulas without noticing, you may overlook a trend or magnify the significance of a result.
Origins of Increased Anion Gap Metabolic Acidosis
A high anion gap value is most commonly associated with metabolic acidosis caused by the rise of acids that are not typically measured on routine labs. This is a key finding in many forms of acid-base abnormality and often triggers a deeper search for the source of the acid load.
Two classic causes are lactate buildup and ketone-related acidosis. In lactic acidosis, the body creates excess lactate due to reduced oxygen delivery, impaired metabolism, or other stress states. In ketoacidosis, ketone bodies collect, often in the setting of insulin deficiency, prolonged fasting, or severe illness.
Other causes can include toxins, kidney failure, or severe tissue breakdown, but the key concept is the same: extra acid enters the system, bicarbonate is consumed, and the anion gap rises. This is why the anion gap is such a useful diagnostic tool in metabolic evaluation.
When reviewing a high value, clinicians often combine the anion gap with a blood gas and serum bicarbonate level to assess severity and to determine whether the acidosis is compensated or worsening.
Sources of Normal Anion Gap Metabolic Acidosis
A normal calculated gap cannot rule out acidosis. In fact, a frequent pattern is hyperchloremic acidosis, where bicarbonate decreases but chloride increases to preserve charge balance. This results in a normal calculated gap even though the patient still has an acid–base disorder.
One common cause is gastrointestinal fluid loss, which leads to loss of bicarbonate from the gastrointestinal tract. Another significant cause is tubular acidosis, a group of disorders in which the kidneys fail to handle acid and bicarbonate properly. In both cases, the body loses bicarbonate and chloride climbs relative to the change, keeping the gap in the reference range.
Because of this, a normal number should not end the evaluation if the patient appears clinically acidotic. The broader pattern of lab findings, symptoms, and blood gas data may still point to a serious acid-base problem.
Calculating the Anion Gap with Albumin
Albumin is a key not directly measured negative ions in the blood, so variations in albumin can change the apparent anion gap. When a patient has hypoalbuminemia, the measured gap may look lower than it truly is. This is why albumin correction is often recommended in clinical settings.
A modified anion gap can reveal concealed acid accumulation that would otherwise be undetected. If albumin is low, the measured gap may underestimate the severity of an underlying metabolic problem. In that setting, using an albumin correction increases the reliability of the result and supports the interpretive value of the calculator.
Exact adjustment is based on the method employed by the testing lab or reference standard, but the principle is the same: decreased albumin means fewer not directly measured negative charges, so the reported gap can seem deceptively within range. Accounting for albumin gives a more reliable view for clinical assessment.
For that reason, an anion gap calculator is especially helpful when it allows the user to evaluate albumin alongside sodium, chloride, bicarbonate, and potassium. Such a combination offers a more complete interpretive framework.
How to Interpret Results in Clinical Context
The anion gap should routinely be understood together with the remainder of the patient picture. A value from a calculator output is not a determination by itself on its own. Rather it is one clue in a wider clinical correlation process that may cover signs, current medications, physical examination findings, arterial blood gas results, and additional laboratory checks.
As an example, a patient with low serum bicarbonate, elevated anion gap, and clinical signs of illness may have a serious metabolic condition. One more patient with the same result but unremarkable blood gas values and no symptoms may need only monitoring or additional review of testing methods.
The clinical picture also plays a role when the result is close to the lab reference range. Small shifts in chloride or bicarbonate can move the calculated value up or down, especially if the analyzer or collection method adds variability. That is why a good anion gap calculator supports interpretation, but never replaces clinical judgment.
Frequent Pitfalls While Using an Anion Gap Calculator
Several analysis pitfalls can lead to misunderstanding when using an anion gap calculator. A frequent issue is measurement variance, which may come from sample processing, analyzer variation, or incorrect entry of the lab values. Just a small error in sodium, chloride, or bicarbonate can change the final number.
Another mistake is ignoring the laboratory reference range. A result that seems unusual in one setting may be normal in another because each laboratory sets its own reference interval. If you are reviewing results across systems, always verify whether the calculator uses the same method and whether it is reporting a potassium-inclusive or traditional result.
A third issue is assuming that every elevated result means the same thing. The anion gap is a helpful clinical tool, but it must be paired with other data to determine whether there is true metabolic acidosis, a mixed disorder, or a lab artifact. A careful review of the serum chemistry panel, blood gas, and history helps avoid overinterpretation.
Lastly, users sometimes overlook albumin status. Without albumin adjustment, a patient with hypoalbuminemia may have a deceptively normal or low anion gap. Recognizing that possibility improves the quality of clinical interpretation.
FAQ
What is an anion gap calculator with potassium?
An anion gap calculator with potassium is a resource that calculates the anion gap using sodium, chloride, bicarbonate, and optionally potassium. It helps assess electrolyte levels and supports evaluation of acid-base balance and possible metabolic acidemia.
How do you calculate the anion gap with potassium included?
Use the potassium-based equation: sodium plus potassium minus chloride and bicarbonate. In equation form, it is anion gap = sodium + potassium - (chloride + bicarbonate). Make sure the numbers come from the same serum chemistry panel.
When should potassium be included in the anion gap formula?
Potassium may be added when the calculator or reference source uses the potassium-inclusive approach, or when a clinician wants to compare results using that method. The choice should be the same each time because formula differences can affect the anion gap value and its clinical interpretation.

What is the meaning of a high anion gap?
A high anion gap often suggests an increase in unmeasured acids and is commonly seen in metabolic acidosis. Important causes include lactic acidosis and ketoacidosis. The result should be interpreted with the blood gas, serum bicarbonate, and overall clinical picture.
Does it need to be the anion gap be corrected for albumin?
Yes, in many cases it should. Hypoalbuminemia can make the gap appear lower than it really is, so albumin correction may reveal a more accurate corrected anion gap. This is especially helpful when the result seems unexpectedly normal despite signs of acidosis.