
What Is the Anion Gap?
The anion gap is a helpful blood chemistry measurement intended to evaluate the equilibrium between positively charged and negative electrolytes. It is not a exact measurement of a single substance; instead, it is a derived value that helps clinicians understand an acid-base problem, especially when the body presents with metabolic acidosis.
In plain terms, the anion gap reflects the variance between the main measured cations and anions in the blood. The typical components are sodium, chloride, and bicarbonate. Because the body seeks to maintain electrical neutrality, any change in these measured values can indicate an underlying imbalance or unseen acid.
This is why the anion gap is important in assessment and medical evaluation. It does not reveal the whole story by itself, but it can assist identify whether an abnormal result is likely due to an acid-base disorder, an electrolyte imbalance, or another metabolic state that needs more care.
How the Anion Gap Formula Uses Sodium
An anion gap calculator typically uses a typical formula based on sodium, chloride, and bicarbonate. The most widely used version is:
Anion gap = sodium - (chloride + bicarbonate)
Some laboratories include potassium in the formula, but the sodium-based version is the preferred one. In this calculation, sodium is the primary measured cation, while chloride and bicarbonate are the primary measured anions. The result helps estimate the amount of unmeasured ions in the blood.
Sodium matters because it is the biggest contributor on the left side of the formula. Even so, sodium is usually interpreted in combination with the rest of the electrolyte panel rather than alone. A normal sodium value does not automatically mean the anion gap is normal, and a sodium abnormality does not always create a major change in the calculation.
The real value of the formula is in interpretation. If sodium, chloride, and bicarbonate move in certain patterns, the calculation can reveal clues about acid-base balance, blood chemistry changes, and the presence of hidden acids such as lactate or ketones.
Why Sodium Shifts Can Affect the Anion Gap
Variations in serum sodium can alter the anion gap, but the effect is determined by the broader picture in the lab values. In hyponatremia, sodium is decreased, which can lower the calculated gap if chloride and bicarbonate do not change in the same way. In hypernatremia, sodium is elevated, which can boost the calculated value if the other components remain unchanged.
That said, sodium does not operate on its own. The anion gap is a ratio-like comparison of measured ions, so the interpretation depends on the complete measurement context. A patient with low sodium may still have a high anion gap if bicarbonate drops substantially because of an underlying acid load. Likewise, a patient with high sodium may also have a normal anion gap if chloride and bicarbonate shift in a balancing way.
This is why clinicians look at the entire lab values pattern. A sodium change can influence the calculation, but the clinical significance comes from the larger blood chemistry picture rather than from sodium alone.
Revised Anion Gap and Albumin Correction
Albumin is a single of the key unmeasured anions in the blood. It is also a primary binding proteins component in circulation, so low albumin can make the anion gap appear lower than it really is. This is the point at which the corrected anion gap becomes helpful.
In hypoalbuminemia, the body has fewer negatively charged albumin present. Because the anion gap depends on maintaining electrical neutrality, the calculated value may fall even when there is a clinically important acid-base issue present. Correcting for albumin helps show whether the apparent normal or low result is hiding a true abnormality.
Albumin adjustment matters more than many people realize. A patient can have a seemingly normal anion gap on paper, yet still have a hidden high gap once the calculation is recalculated. This is especially important in diagnostic workups where the goal is to determine the patient’s actual acid-base status rather than just accept the raw number at face value.
For that reason, the corrected anion gap is often viewed as part of a thorough interpretation, particularly when albumin is low or when the clinical picture does not align with the lab result. It gives a more accurate view of whether the blood is showing a real acid-base imbalance.
Interpreting a Elevated, Typical, or Low Anion Gap
Knowing whether the result is high anion gap, normal anion gap, or low anion gap is central to evaluation. Each result pattern suggests different explanations, and the reference range provided by the lab is essential for context.
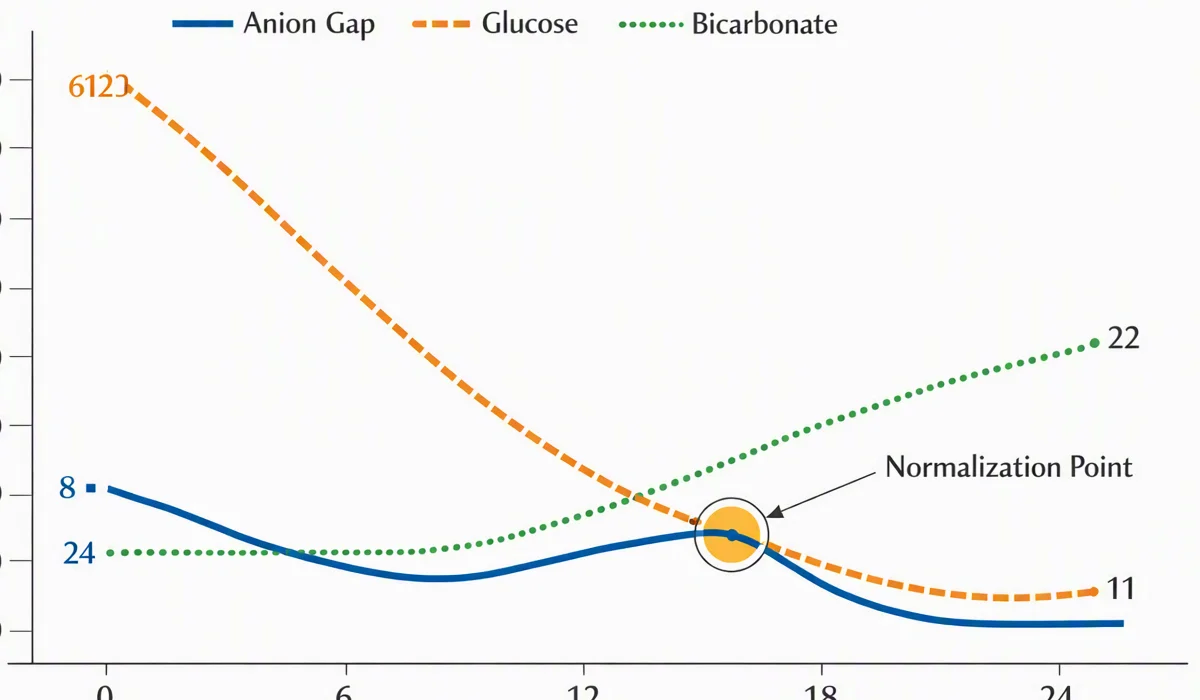
A high anion gap often points toward metabolic acidosis caused by unmeasured acids in the blood. Common causes include lactic acidosis, diabetic ketoacidosis, and renal failure. In these cases, bicarbonate is depleted as the body tries to buffer excess acid, which widens the gap.
A normal anion gap does not rule out disease. It may be seen in some forms of metabolic acidosis where bicarbonate loss is offset by chloride rise, creating a balanced calculation even though the patient still has an acid-base disorder. This is why a normal result must still be interpreted in the context of symptoms and other lab findings.
A low anion gap is less common and can occur with hypoalbuminemia, lab error, or unusual changes in measured ions. It may also reflect analytical issues or shifts in blood chemistry that reduce the apparent difference between cations and anions. A low result should never be dismissed automatically; it deserves careful review of the full electrolyte panel and measurement conditions.
In all three cases, the number is a clue rather than a final answer. The diagnosis depends on the broader clinical picture, including the patient’s acid-base balance, serum levels, and other markers of metabolic state.
Frequent Clinical Situations In Which Serum Sodium and Anion Gap Rise Together
Some medical scenarios help clarify the relationship between sodium and anion gap more apparent. One typical example is dehydration. As body water is lost, sodium may become more concentrated, and the overall lab pattern can shift. Based on the severity and accompanying electrolyte changes, the anion gap may go up, remain stable, or appear altered because of concurrent changes in chloride and bicarbonate.
Renal failure is an additional important example. When the kidneys cannot remove acids effectively, unmeasured acids accumulate and the anion gap can rise. Sodium may also be abnormal in renal dysfunction, but the anion gap elevation is usually driven more by acid retention than by sodium alone.
Lactic acidosis is a classic cause of high anion gap metabolic acidosis. When tissue oxygen delivery is impaired or metabolism shifts, lactate rises, bicarbonate falls, and the gap increases. Sodium may be normal, low, or high depending on fluid status, but it is not the main driver of the abnormality.
Diabetic ketoacidosis also often produces a high anion gap. Ketone accumulation consumes bicarbonate and creates a clear acid-base disturbance. Sodium can appear lower than expected in this setting because of osmotic effects and fluid shifts, which is why the overall interpretation must consider the electrolyte https://anion-gap-range805.almoheet-travel.com/how-to-estimate-anion-gap-from-cmp-results panel as a whole.
Together, these examples highlight a key principle: sodium and the anion gap may change together in some metabolic states, but the relationship is indirect. Most often, the sodium change reflects the patient’s fluid and metabolic state, while the gap reflects the presence of unmeasured acid.
How to Use an Anion Gap Calculator Correctly
When using an anion gap calculator correctly begins with the appropriate data. The calculator should be based on a recent electrolyte panel that includes sodium, chloride, and serum bicarbonate. If the values come from separate time points, the calculation may not show the patient’s actual status.
To get meaningful results, consider the relevant lab panel and the units used. Small differences in measurement technique or reference method can influence interpretation. The calculator is helpful for rapid screening, but the result should always be compared with the lab reference range and the patient’s clinical picture.
Proper interpretation also means considering more than the number itself. Ask whether albumin is low, whether the patient has evidence of metabolic acidosis, and whether the acid-base pattern fits the story. A calculated value is only one piece of the evaluation, and it works best when combined with other blood chemistry markers.
In practice, the best use of the calculator is to support clinical reasoning. It helps identify whether a result needs additional evaluation, whether a corrected anion gap should be considered, and whether the electrolyte panel suggests a hidden imbalance that requires further assessment.
Frequently Posed Inquiries About the Anion Gap and Sodium
Does sodium actually change the anion gap?
Sodium affects the anion gap because it is included in the formula, but it does not usually control the result by itself. The calculation also depends on chloride and bicarbonate, so the full pattern is more important than sodium alone. A shift in sodium may shift the number, but interpretation still requires the full blood chemistry context.
Why is sodium included in the anion gap formula?
Sodium is included because it is the principal measured cation in the formula. The anion gap compares sodium against chloride and bicarbonate to estimate the amount of unmeasured ions. This helps assess acid-base balance and detect hidden acids that may not be obvious from a basic lab panel.
Can a low sodium level cause a high anion gap?
Usually not on its own. Hyponatremia can influence the calculation, but a high anion gap is more often caused by increased unmeasured acids such as lactate or ketones. In other words, low sodium may affect interpretation, but it is not the classic cause of a high gap.
How does albumin affect the anion gap calculation?
Albumin is a key unmeasured anion, so low albumin can make the anion gap appear lower than it really is. That is why the corrected anion gap is helpful in hypoalbuminemia. Adjusting for albumin enhances interpretation and helps maintain the meaning of the result.
When should an anion gap calculator be used with other lab values?
It should always be used with other lab values, especially sodium, chloride, bicarbonate, and albumin. The calculator is most helpful when reviewed alongside the full electrolyte panel and the patient’s symptoms. That combination gives the strongest opportunity of identifying a true acid-base disorder, lab pattern, or metabolic imbalance.