The expected anion gap for infants is generally close to yet not necessarily identical to the adult range. In many pediatric interpretation settings, the anticipated normal range is roughly 8 to 16 mEq/L, though the specific pediatric reference range is influenced by the laboratory, the child’s age, and whether the result is corrected for albumin. As a result, a result should consistently be read in the clinical context of the infant’s overall health, symptoms, and other blood chemistry panel findings.
The anion gap is a useful calculated measurement that is used to assess electrolyte balance and acid-base status. It is often used as a diagnostic clue when searching for a possible metabolic disturbance. An Anion Gap Calculator can make the arithmetic easier, but the real value comes from understanding what the number means in an infant, especially when the serum sodium, serum chloride, and serum bicarbonate levels are shifting during illness or recovery.
What Is the Anion Gap?
The anion gap is a laboratory value obtained from common electrolytes analyzed in a blood sample. It estimates the difference between the major positive ions and the major negatively charged ions in the blood. In practical terms, it helps clinicians think about whether there are unmeasured acids or other substances influencing the body’s buffering system.
The usual version of the calculation uses sodium, chloride, and bicarbonate. Because these values are part of a routine serum chemistry panel, the anion gap is not directly measured. Instead, it is a calculated measurement based on other lab results. That is why the anion gap formula is so important for accurate interpretation.
In plain language, the anion gap helps show whether the difference between the measured cations and anions is within the expected range. When the result is abnormal, it may point to an underlying cause such as acid accumulation, albumin changes, or a testing issue. However, one value alone does not diagnose a condition. It is only one piece of the larger picture of acid-base status and overall health.
Typical Anion Gap Range for Infants
The normal anion gap for infants is commonly viewed close to the pediatric-plus-adult reference interval reported by numerous laboratories. A common expected range is about 8 to 16 mEq/L, though different laboratories may report slightly different limits. Because newborn physiology is still adjusting after birth, the exact reference interval can vary by maturation, feeding pattern, and lab method.
For newborns, values may shift somewhat during the first days of life. This is why the result should be interpreted using an developmentally appropriate pediatric reference range rather than assuming a single universal number applies to every infant. The lab’s own report is often the ideal first reference for interpretation.
Another important detail is that the anion gap can be influenced by the serum bicarbonate level. When bicarbonate is lower, the gap may rise if the body is responding to an acid load. When bicarbonate is higher or chloride changes in the opposite direction, the gap may appear lower. That means the same number can have different meanings depending on the full chemistry pattern.
For this reason, a normal result does not always rule out illness, and an abnormal result does not always mean severe disease. The number must be viewed alongside the infant’s symptoms, hydration status, feeding history, and other blood chemistry panel results.
How an Anion Gap Calculator Operates
An Anion Gap Calculator uses a simple calculation formula based on measured lab values. The most common formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
This equation takes the serum sodium value and subtracts the sum of serum chloride and serum bicarbonate. The result is the computed value called the anion gap. Because the calculation is derived from routine lab data, it is often available quickly once the chemistry panel is complete.
Some calculators may also offer a correction for albumin, since low albumin can lower the measured gap. That makes the tool especially useful in pediatric interpretation, where changes in protein levels and fluid balance can affect the result. Even so, the calculator is only as accurate as the numbers entered, and it cannot take the place of medical judgment.
When using an Anion Gap Calculator, it helps to remember these considerations:
- The calculation depends on accurate serum sodium, serum chloride, and serum bicarbonate values. The result is a calculated measurement, not a directly measured laboratory value. Age, albumin, and the clinical context affect interpretation. Small differences can occur because of measurement variability between laboratories.
So, while the calculator can quickly show the number, https://ameblo.jp/anion-gap-formula852/entry-12977277435.html the meaning of that number depends on whether the infant’s acid-base status and overall laboratory pattern match a certain condition.
Why Infant Ranges May Differ From Adults
Infant results are not always interpreted exactly the same way as adult results because of age-specific reference ranges. Babies are still maturing kidney function, fluid regulation, and metabolic control, and these factors can affect the chemistry panel. In newborns, this is especially the case because the body is shifting from fetal to postnatal life.
Pediatric patients often have different expected laboratory patterns than adults due to growth, feeding changes, and developmental physiology. The kidneys, lungs, and liver all work in maintaining the body’s electrolyte balance and buffering system, and those systems are still maturing in early life. As a result, the same laboratory value can have a different interpretation in an infant than it would in an older child or adult.
Albumin is also important. Because albumin holds negative charge in the blood, lower levels can decrease the anion gap without necessarily indicating a dangerous condition. This is one reason clinicians may consider corrected interpretation when hypoalbuminemia is present. The result may look low simply because less albumin is available to participate to the charge balance.
In addition, mild differences in method, specimen handling, or analyzer calibration can lead to measurement variability. That is why a single laboratory value should not be read in isolation. A careful pediatric interpretation examines trends, symptoms, and other labs together.
How a High Anion Gap May Point To
A high anion gap is often an important sign to metabolic acidosis. This indicates the body may have too much acid or too little bicarbonate available to buffer acid. Among infants, this finding often prompts careful review of feeding, hydration, perfusion, and overall illness severity.
One possible cause is lactic acidosis. Lactic acid can rise when tissues are not getting enough oxygen or when the body is under significant stress. Another cause is ketosis, which may occur when an infant is not taking in enough calories, is vomiting, or has another condition affecting glucose use. In these situations, the anion gap helps point toward an underlying cause of the metabolic disturbance.
Renal failure is another important cause because the kidneys normally help eliminate acids from the body. If kidney function is reduced, acids can accumulate and push the gap upward. Other disorders can also contribute, but the main point is that a high number often suggests acid accumulation rather than a simple electrolyte shift.
When the gap is high, clinicians often check the full blood chemistry panel, including bicarbonate, creatinine, glucose, and chloride level. The result is best interpreted as a diagnostic clue, not a final diagnosis. A metabolic acidosis pattern in an infant should always be interpreted with the child’s symptoms and exam findings.
What a Low Anion Gap May Suggest
A low anion gap is not as common than a high one, but it can still be significant. One of the primary explanations is hypoalbuminemia. Since albumin contributes anionic particles, low albumin can reduce the gap even when the infant is otherwise well.
Another possibility is lab error. Because the anion gap is calculated from multiple measurements, a small issue in one component can alter the final value. If the result does not match the infant’s condition, repeat testing or review of specimen handling may be warranted.
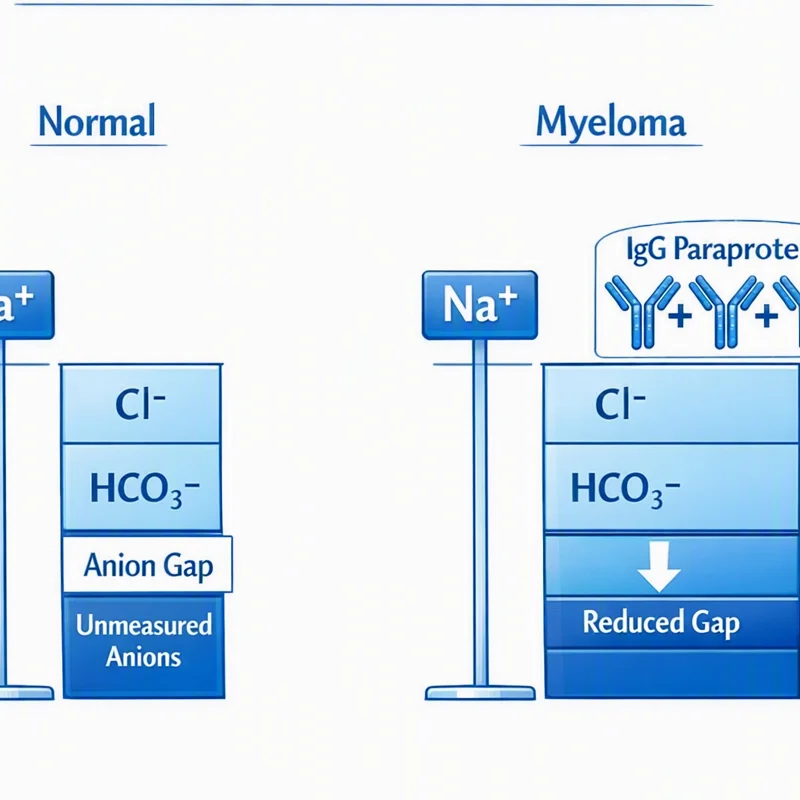
Paraproteinemia is a less common cause in infants, but it is part of the wider differential for a low result. Another cause is hyperchloremia, in which the chloride level is relatively high compared with sodium and bicarbonate. That shift can shrink the calculated difference and make the gap appear low.
When a low gap is found, clinicians often ask whether the number matches the rest of the lab picture. Is the infant properly hydrated? Are other values normal? Is there a known protein abnormality or a reason for low albumin? These questions help determine whether the low value is clinically relevant or simply a reflection of measurement conditions.
When to Ask a Pediatric Clinician
If an infant has unusual blood chemistry panel results, a pediatrician or other pediatric clinician should review them. This is especially important when the anion gap is outside the expected range or when the infant has alarming clinical symptoms such as poor feeding, vomiting, lethargy, rapid breathing, dehydration, or changes in alertness.
A medical professional can place the result into the correct clinical context, check whether the values match the baby’s age, and decide whether further testing is needed. A single abnormal result does not always mean something serious, but it should not be ignored if the infant seems ill.
Obtain a medical evaluation when the laboratory value is clearly abnormal, when symptoms are present, or when the result does not match the child’s condition. The clinician may go over repeat chemistry testing, glucose, blood gas results, kidney markers, and albumin to understand the full picture.
In short, the anion gap is useful because it can reveal a hidden problem, but it is not a stand-alone diagnosis. The combination of the laboratory value, age-specific expectations, and the infant’s overall condition is what shapes care.
Frequently Asked Questions
What is considered a normal anion gap for infants?
A normal anion gap for infants is often around 8 to 16 mEq/L, but the exact normal range depends on the laboratory and the infant’s age. The result should be interpreted using the lab’s pediatric reference range and the child’s overall health picture.
Is the anion gap different in newborns compared with older infants?
Yes, it can be. Newborns may have slightly different laboratory patterns during the first days of life, so the reference range can differ from that used for older infants. Age-specific reference ranges are important for accurate interpretation.
How do you calculate the anion gap using an Anion Gap Calculator?
An Anion Gap Calculator typically uses the anion gap formula: serum sodium minus the sum of serum chloride and serum bicarbonate. The calculator returns a calculated value that helps assess acid-base status, but the interpretation depends on the full lab picture.
Can a regular anion gap still be present with illness in an infant?
Absolutely. A normal result does not exclude a medical problem. An infant can still have signs or an additional issue even if the anion gap is within the normal range. Clinical interpretation always depends on the complete set of clinical information, not just one individual laboratory value.
When should a elevated or low anion gap in an infant be checked by a doctor?
A increased or reduced anion gap should be checked by a doctor when it is abnormal, when the infant has signs of illness, or when the value does not align with the rest of the blood test results. A pediatrician can decide whether repeat testing or more medical assessment is needed.